


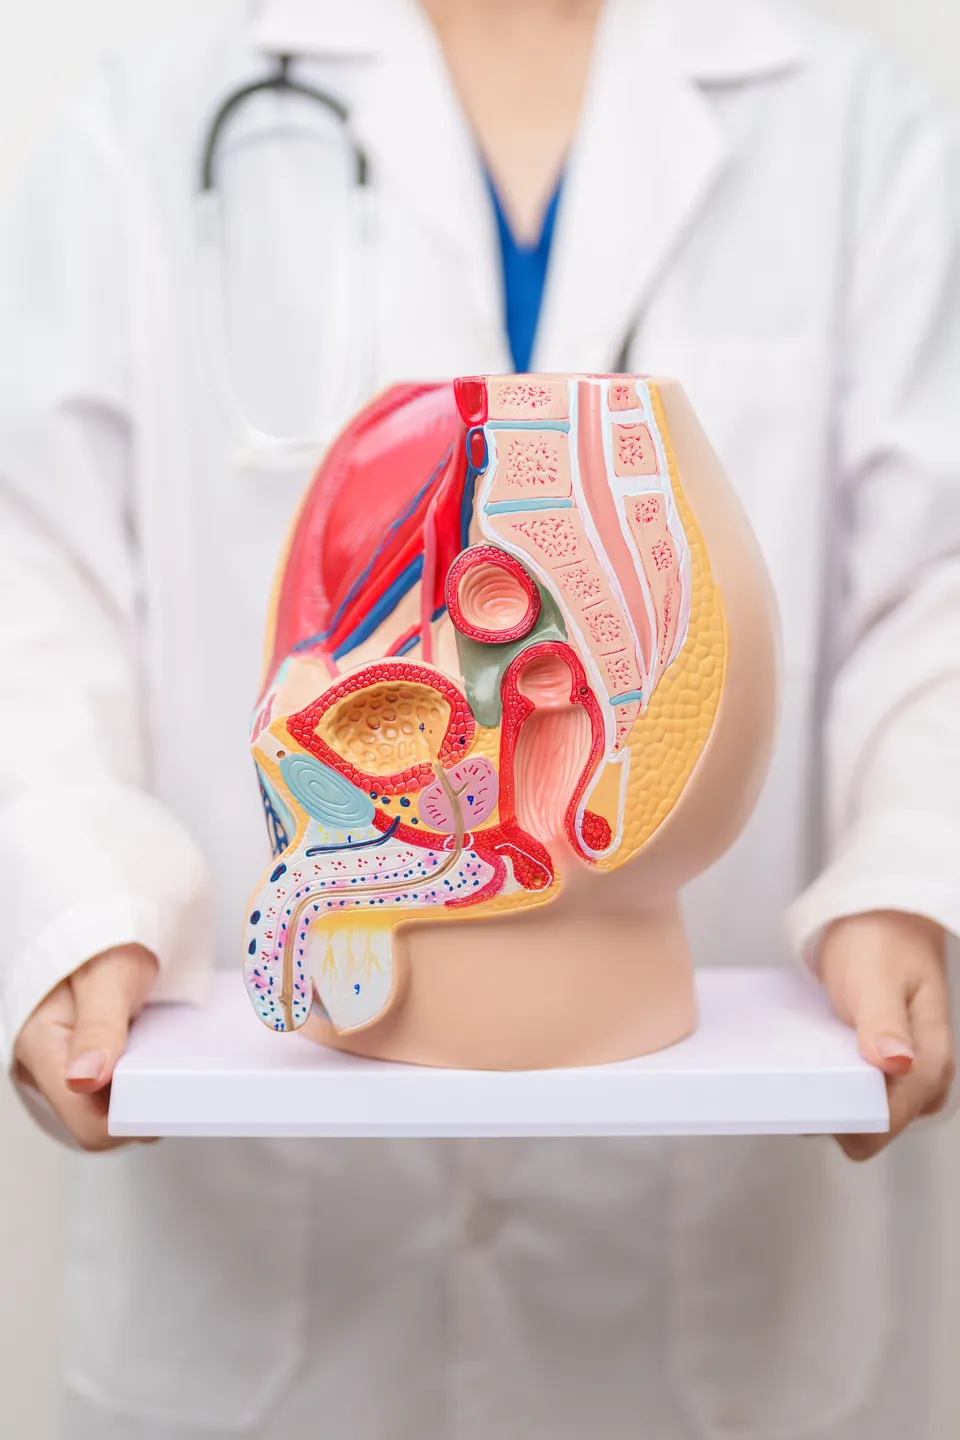
How are varicocele and male infertility related? When treatment is and is not considered, the methods, the evidence and the period after the procedure.
Varicocele is the enlargement of the veins that return blood from the testis to the heart, and this enlargement can affect sperm production. But having a varicocele does not mean you are infertile; nor does every varicocele need treatment. To decide on treatment, the type of varicocele, your semen result and your general situation are looked at together. The information below offers a general framework; it does not replace a diagnosis or treatment recommendation specific to you.
What is varicocele?
Varicocele is the enlargement of the network of veins surrounding the testis in the scrotum. It often gives no symptoms; it is usually noticed at examination or during an infertility investigation. For this reason varicocele is mostly considered when pregnancy is delayed or when your semen analysis comes out abnormal.
A varicocele noticed by hand or by eye at examination is called a "clinical varicocele". The type that can be seen only with imaging methods such as ultrasonography and cannot be felt at examination is called a "subclinical varicocele". This distinction determines the decision on treatment.
If there is a varicocele, does it become harder to have children?
It is thought that varicocele can adversely affect sperm production. But this relationship is not the same for everyone: in a proportion of men with a varicocele the semen result stays normal, and these men can have children. For this reason varicocele is regarded not as the only cause of infertility but as one of the possible causes; your other findings are also investigated.
How is the diagnosis made?
The diagnosis starts with your doctor's examination. At the examination the state of your testes and veins is looked at. Scrotal ultrasonography can help the diagnosis. Guidelines on this subject recommend scrotal ultrasonography in infertile men because of the risk of testicular cancer; but in unexplained infertility with a normal semen analysis, routine testicular imaging is not recommended. These two recommendations are for different groups.
Semen analysis is an integral part of the diagnosis. In the decision on treatment, what matters most is whether your semen result is normal. Results are not based on a single sample; if necessary, a repeat assessment is made.
When is treatment considered, and when not?
According to guidelines on this subject, varicocele treatment is considered if all the following conditions are present together: a varicocele found at examination (clinical), abnormal semen values, infertility with no other explanation, and good ovarian reserve in the woman. If your semen analysis is normal, or your varicocele is of the type found only with imaging (subclinical), treatment is not recommended.
Current guidelines draw a similar framework: in clinical varicocele, surgical or radiological treatment may be preferred over waiting; those with abnormal semen values may benefit more from it. But this recommendation is a conditional one and the data behind it are not yet strong.
Another situation is the co-existence of high sperm DNA damage with unexplained infertility or with failure of assisted reproduction treatment. In this case too, treating the varicocele may be an option, but this recommendation is also a weak one.
What is the aim of varicocele treatment?
The aim of treatment is to close the enlarged vein pathway. The main approaches are surgical and radiological methods.
How are surgery and microsurgery performed?
In surgery the enlarged veins are tied off. This can be done by open surgery, by laparoscopy or under the operating microscope. Which technique is chosen is decided by the doctor who looks after you.
How is embolisation performed?
In the radiological method (embolisation), instead of an operation, the enlarged vein is closed by entering through a vein; the procedure is done under imaging guidance. Because contrast material is used, risks specific to this method, such as contrast allergy, are also assessed.
What does the evidence say?
According to reviews on this subject, the likelihood of achieving pregnancy may be higher in those who have varicocele treatment compared with those who have no treatment or whose treatment is delayed; but this finding is not yet definitive. The effect of treatment on live birth is uncertain, and the data on this are very limited. In other words, treatment may increase the likelihood of pregnancy, but does not guarantee the result.
The data on differences between the techniques are also limited. Current guidelines recommend, although with low certainty, that the microscopic surgical technique be preferred over other surgical techniques. It is stated that the frequency of problems such as hydrocele (a collection of fluid around the testis) and recurrence changes with the technique; but these comparisons too rest on limited data. For this reason no definite conclusion can be reached on the choice of technique; the decision is made with your doctor according to your situation.
What can happen after the procedure?
After the procedure, mild pain, mild swelling of the scrotum and mild bruising may be seen. These are expected findings; they can be relieved with painkillers and lessen over time.
The problems that can be seen after the procedure are as follows:
- Hydrocele: A collection of fluid around the testis.
- Haematoma: A collection of blood at the site where the vein was closed.
- Infection: Redness, discharge and fever at the incision or procedure site.
- Recurrence: The varicocele appearing again.
- Contrast allergy: A reaction to the contrast material used in the radiological method.
How often these problems are seen varies from method to method and from person to person. The risks and benefits of the procedure are discussed with the doctor before the procedure.
Treatment, or an assisted reproduction technique?
The choice between varicocele treatment and an assisted reproduction technique is not determined by the varicocele alone. The woman's age and ovarian reserve, the duration of trying for pregnancy and the semen result are assessed together. This is also why "good ovarian reserve in the woman" appears among the conditions for treatment. If the woman's age is advanced or her reserve is limited, the time to be waited after treatment can lengthen the couple's overall process; in this case the doctor may recommend assisted reproduction techniques directly instead of waiting after varicocele treatment.
Independently of varicocele treatment, lifestyle adjustments such as weight control, stopping smoking and reducing alcohol are also recommended for sperm quality. If anabolic steroids are being used, this should be reported to the doctor.
Frequently Asked Questions
When is the spermiogram repeated after the operation?
Because the sperm production cycle takes time to complete, the follow-up analysis is not done straight after the procedure; a period set by your doctor is waited. Because this period can vary from person to person, do not expect an exact date, and follow your doctor's plan.
Is there a difference between embolisation and surgery in terms of pregnancy?
According to the data on this subject, whether there is a difference between surgery and radiological treatment in terms of pregnancy is uncertain; the data are insufficient. Because side-effect data are also limited, the choice is made according to your situation and your doctor's assessment.
Is a varicocele treated in adolescence?
Not in every adolescent. Current guidelines tie surgery in adolescence to certain criteria; whether these criteria are met is decided by the doctor who looks at the adolescent's situation, and monitoring is often an option too.
Does having a varicocele mean I am infertile?
No. The semen results of some men with a varicocele are normal, and they can have children. A varicocele is assessed together with your other findings.
Is treatment needed for a varicocele seen only on ultrasound?
No. Treatment is not recommended in those whose semen analysis is normal, or in a subclinical varicocele found only with imaging.
Is the decision for treatment made only according to the examination result?
No. A clinical varicocele, abnormal semen values, infertility with no other explanation and the woman's ovarian reserve are assessed together. The couple's general situation influences the choice of treatment.
Does varicocele surgery guarantee pregnancy?
No. Treatment may increase the likelihood of pregnancy, but this finding is not definitive. The effect on live birth is also uncertain.
Is microsurgery definitely the better option for everyone?
No definite conclusion can be drawn. Although guidelines recommend preferring microscopic surgery over other surgical techniques, the certainty of the data is low. You choose the technique together with your doctor.
Can swelling and bruising occur after the procedure?
Yes. Mild pain, mild swelling of the scrotum and mild bruising may be seen; these may lessen over time. You should talk about the risks of the procedure and the period afterwards with your doctor.
Is varicocele treatment always done before assisted reproduction treatment?
No. The woman's age and ovarian reserve, the duration of trying and the semen result are assessed together. In situations where waiting could lengthen the overall process, the doctor may recommend assisted reproduction techniques directly.
Do I need to mention the anabolic steroids I use?
Yes. Report your use of anabolic steroids to your doctor. Lifestyle and the products used are also discussed during the assessment.
Can a varicocele appear again after the procedure?
Yes. Recurrence is one of the problems that can be seen after the procedure. Risks such as hydrocele, haematoma and infection also vary with the method and the person.
Get Your Free Consultation
Fill out the form below and our team will contact you

