


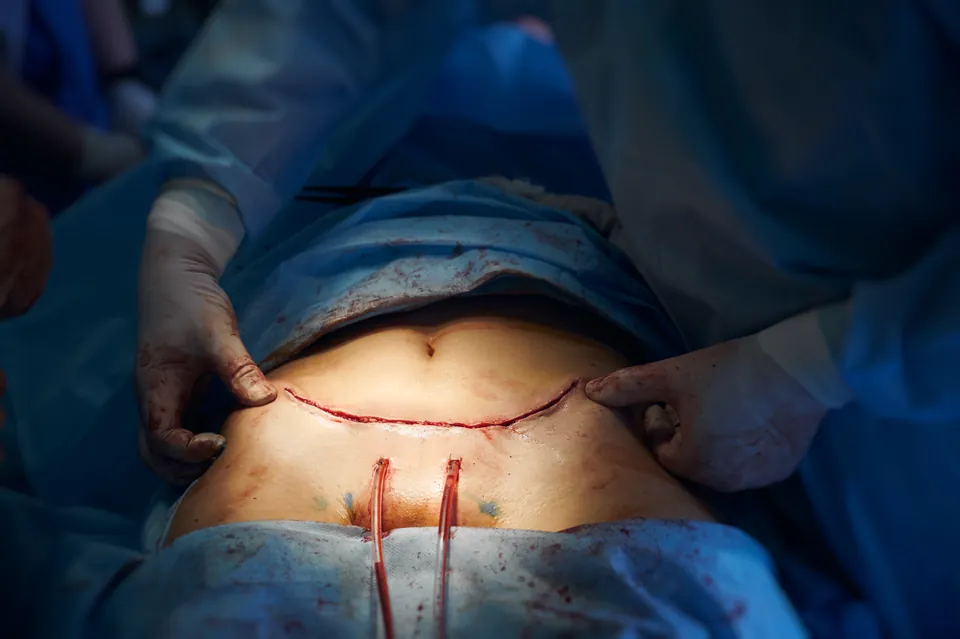
What is open hysterectomy (abdominal hysterectomy) and when is the open route chosen? Information on the ovaries, menopause, risks and recovery.
Open hysterectomy (abdominal hysterectomy) is an operation in which the uterus is removed through an incision made in the abdomen. Once the uterus is removed, the possibility of becoming pregnant and carrying a pregnancy comes to an end, and menstrual bleeding stops. For this reason, the decision for surgery takes into account the severity of your complaints, the other treatments that could be tried and your own preferences together. Whether the ovaries are removed is a separate decision. Here you will find a general framework; this information does not replace the individual assessment made for you.
What is open hysterectomy?
Hysterectomy is the removal of the uterus. In the open method an incision is made in the lower abdomen, the uterus is separated from the tissues attached to it and removed, and the upper end of the vagina is closed with stitches. The removed uterus is sent to pathology.
Is the cervix also removed?
If the cervix is removed together with the uterus, the operation is called total hysterectomy; if the cervix is left in place, it is called subtotal hysterectomy. Some studies have reported that period-like bleeding is seen more often for a time after the operation in people whose cervix is preserved. If the cervix is left in place, your doctor will plan for smear screening to continue.
In which situations is hysterectomy considered? What are the alternatives?
Hysterectomy is generally considered when complaints caused by bleeding, pain or structural problems of the uterus cannot be controlled sufficiently in other ways. Medicines and procedures that preserve the uterus are often tried first. If cancer is suspected, different planning is needed; the scope and method of the operation are determined separately. It is important to discuss the alternatives with your doctor before deciding.
Why might the open route be chosen?
The uterus can be removed from inside the abdomen by the open or closed route, or through the vagina. In benign conditions the method is chosen according to the characteristics of the uterus and vagina, any accompanying disease, whether an additional procedure is needed, the surgeon's training and experience, the facilities of the hospital and your preference. The open route may be considered particularly in the following situations:
- If the uterus is very large
- If widespread adhesions are expected in the abdomen
- If other procedures are also planned in the same operation
- If extensive planning is needed because cancer is suspected
- If the feasibility of the other routes is limited
The vaginal and closed routes have been found to be associated with a faster return to daily life and fewer wound infections than open surgery; the open route is associated with a longer hospital stay and a longer recovery. It has also been reported that the likelihood of injury to the urinary tract, including the ureter, is higher with the laparoscopic route than with the open route. These findings rest on moderately reliable data and do not mean that the open route is unnecessary; the choice of method is made according to you.
What is done before the operation?
Preparation starts with a gynaecological examination and ultrasound; other imaging methods are also used when needed. Your doctor decides which examinations of the cervix and the lining of the uterus are needed. During the blood count, pregnancy test and anaesthetic consultation, you should tell your doctor about the medicines you use, your allergies and the operations you have had. The surgical team explains when to stop eating and drinking, which medicines to pause and whether bowel cleansing is needed. Measures to prevent clot formation in the leg veins after the operation are also planned before the operation, according to your level of risk.
How is the operation performed?
Which anaesthetic is used depends on the assessment of the surgical and anaesthetic team. The abdominal cavity is reached through an incision in the lower abdomen; the ligaments and blood vessels that hold the uterus to the surrounding tissues are separated, bleeding is controlled and the uterus is taken out. The upper end of the vagina is then stitched and the abdominal wall is closed in layers. The place and shape of the incision vary with the size of the uterus and the scope of the operation. The operation is performed by Assoc. Prof. Dr. Nurettin Türktekin at Memorial Şişli Hospital.
Are the ovaries preserved? What is the effect on menopause?
Removing or preserving the ovaries is a decision separate from removing the uterus. If the ovaries are also removed in a person who has not yet reached menopause, menopausal symptoms start right after the operation. When the ovaries are left in place, there is no menstrual bleeding because there is no uterus, but the ovaries can continue to produce hormones; it has been reported that the age at which menopause begins may move slightly earlier.
Removing the ovaries reduces the risk of ovarian cancer, but when done before menopause it may be associated with cardiovascular disease, bone loss and effects on cognition. In operations performed for benign reasons, removal of the tubes as well can be considered with the aim of reducing the risk of ovarian cancer. The decision about the tubes and ovaries is made at the consultation with your doctor, taking your personal risks into account; whether you need hormone therapy is also discussed with your doctor.
What are the risks of open hysterectomy?
Open hysterectomy is a major operation. The main risks that can be encountered in this operation include the following:
- Risks related to the anaesthetic
- Bleeding and the need for a blood transfusion
- Infection (at the incision site, in the urinary tract, at the upper end of the vagina, in the pelvis)
- Injury to the bladder, ureter, bowel or a blood vessel
- Separation of the stitch line at the upper end of the vagina, or a collection of blood
- Opening of the incision and hernia
- Formation of adhesions inside the abdomen
- Temporary slowing of the bowel
- Difficulty passing urine
- Clot formation in the leg veins
- The end of fertility
- Surgical menopause if the ovaries are also removed
- Rarely, an unexpected pathology result
How often these risks occur varies with the disease, the size of the uterus and the scope of the operation. You can ask your doctor at the pre-operative consultation which of them are more relevant to you.
What are recovery and life after the operation like?
After the operation, pain at the incision site, light vaginal spotting or discharge, tiredness and temporary changes in bowel habit are among the usual symptoms. After open surgery, the hospital stay and recovery time are generally longer than with the vaginal or closed route; the actual time varies with the hospital and the person. The team that performs the operation will give you the instructions on when you can return to daily life, work, sport and sexual intercourse, and on wound care. At the follow-up examination your pathology result is shared and your questions about life after the operation are discussed.
Frequently Asked Questions
What is the difference between total and subtotal hysterectomy?
If the cervix is removed together with the uterus, the operation is called total hysterectomy; if the cervix is left in place, it is called subtotal hysterectomy. When the cervix is left in place, period-like bleeding can be seen more often for a time after the operation; in this case your doctor plans for smear screening to continue.
Are there other treatment options besides hysterectomy?
In most cases medicines and procedures that preserve the uterus are tried first. Hysterectomy is considered when these routes cannot control the complaints sufficiently. It is important to discuss the alternatives with your doctor before deciding.
What routes can be chosen instead of the open method?
The uterus can be removed from inside the abdomen by the open or closed route, or through the vagina. The vaginal and closed routes have been found to be associated with a faster return to daily life and fewer wound infections than open surgery; the open route is associated with a longer hospital stay and a longer recovery. Which route suits you is decided according to the characteristics of your uterus and vagina, any accompanying disease, whether an additional procedure is needed, the surgeon's experience and your preference.
Are the ovaries also removed? How does this affect menopause?
Removing or preserving the ovaries is a decision separate from removing the uterus. If you have not yet reached menopause and your ovaries are also removed, menopausal symptoms start right after the operation. When the ovaries are left in place, there is no menstrual bleeding because there is no uterus, but the ovaries can continue to produce hormones; it has been reported that the age at which menopause begins may move slightly earlier.
Do the tubes also need to be removed?
In operations performed for benign reasons, removal of the tubes as well can be considered with the aim of reducing the risk of ovarian cancer. This decision is made at the consultation with your doctor, taking your personal risks into account.
What examinations are done before the operation?
Preparation starts with a gynaecological examination and ultrasound; other imaging methods are also used when needed. A blood count, a pregnancy test and an anaesthetic consultation are carried out; you should tell your doctor about the medicines you use, your allergies and the operations you have had. Measures to prevent clot formation in the leg veins after the operation are also planned before the operation, according to your level of risk.
How long does recovery take after the operation?
After open surgery, the hospital stay and recovery time are generally longer than with the vaginal or closed route; the actual time varies with the hospital and the person. The team that performs the operation will give you the instructions on when you can return to daily life, work, sport and sexual intercourse.
How is sexual life affected after the uterus is removed?
The effects differ from person to person. Some studies have found no difference in sexual function between total and subtotal hysterectomy. When you can start sexual intercourse will be told to you by looking at the state of the stitch line at the post-operative check; if you have pain during intercourse, you should tell your doctor.
What is done to prevent clots in the legs after the operation?
After gynaecological operations there is a risk of clots in the leg veins; this risk is assessed for you and a preventive plan is made. Early mobilisation, mechanical methods applied to the legs and, when needed, the use of medicines can be part of this plan.
Does smear screening continue after the uterus is removed?
If the cervix was also removed and there has been no high-grade lesion of the cervix in the past, your doctor decides whether you will continue screening. If the cervix is left in place, screening continues. Which group you fall into is determined by your operation report and your past results; do not stop the screening programme on your own.
Will there be bleeding after the operation if the cervix is left in place?
If the cervix has been left in place, you may see period-like bleeding after the operation. In other cases, the duration and nature of any bleeding are assessed at the follow-up examination.
Get Your Free Consultation
Fill out the form below and our team will contact you

